Fundamentals | 20 min read | Beginner
Simon's Two-Stage Design: A Guide to Phase II Clinical Trials
Simon's two-stage design is the usual way to build a futility stop into a single-arm Phase II trial. This guide explains the parameters that define the design, how Type I error and power are controlled, how early termination and expected sample size are calculated, and how optimal, minimax, and admissible designs compare.
What Is Simon's Two-Stage Design?
Simon's two-stage design is a formal design for a single-arm Phase II clinical trial with a binary endpoint such as tumor response. Patients are enrolled in two stages. A first stage of n₁ patients ends in an interim analysis, and the trial stops early for futility if the number of responses is at most r₁. If the interim result is promising, the trial continues to a maximum total of N patients, and the treatment is declared promising only if the total number of responses exceeds r.
It exists to solve a practical problem. A single-arm Phase II trial has to decide whether a response rate is high enough to justify further development, and a single-stage trial answers that question only after every planned patient has been treated. When the treatment is inactive, most of those patients were exposed for nothing. Simon's design places a pre-specified futility decision in the middle of enrollment, so an inactive treatment can be abandoned after n₁ patients while a promising treatment still reaches the full sample size.
Four inputs define the design. First, p₀ and p₁, the null and target response rates the design is built around. Second, the Type I error α and the power 1 − β, which set how strict the evidence must be. A search over feasible two-stage designs then returns boundaries that satisfy those constraints while keeping enrollment small. Everything else in this guide follows from those four inputs.
Many designs satisfy the same constraints, so the method usually reports two named candidates. The optimal design minimizes the expected sample size under p₀: the average enrollment when the treatment is inactive. The minimax design minimizes the maximum sample size N: the most patients the trial can require. A design is admissible when no other feasible design has both a smaller maximum sample size and a smaller expected sample size under p₀, so admissible designs sit between the two extremes and trade one of those quantities for the other. The optimal and minimax designs are the endpoints of that set, which is why the final choice is a judgement rather than a default.
The rest of this guide works through the decision rules, the calculations behind those summaries, a fully worked example, and the trade-offs that decide which candidate belongs in a protocol.
How Simon's Two-Stage Design Works
A Simon's two-stage design is defined by four numbers. They are found by search rather than guessed, but each has a direct reading in the protocol, and the same notation appears in every published design table. The search takes four planning inputs (p₀, p₁, α, and the target power) and returns these four design parameters:
| Parameter | What it fixes |
|---|---|
| n₁ | Patients enrolled before the interim analysis |
| r₁ | Futility boundary: stop after stage 1 if responses are ≤ r₁ |
| N | Maximum total sample size if the trial continues |
| r | Final boundary: declare the treatment promising if total responses are > r |
Stage 1: early stopping for futility
Stage 1 enrolls n₁ patients and counts responses. If the count is at most r₁, the trial stops and the treatment is declared insufficiently promising. Because the rule is written before the first patient is enrolled, the decision cannot drift with what the data appear to show.
How often this happens is a property of the design and of the true response rate, and it is summarized by the probability of early termination. When the treatment is inactive, a high probability of early termination is exactly the point of the design.
Stage 2: the final decision rule
If more than r₁ responses are seen in stage 1, the trial continues and enrolls the remaining patients up to N. When all N patients have been evaluated, the treatment is declared promising only if the total number of responses exceeds r.
Early stopping therefore does not change the final rule: the same threshold r applies to every trial that reaches stage 2. What changes is how many patients are enrolled before the decision is made.
Why both rules are fixed in advance
The two boundaries are chosen together, and neither is free of the other. Moving r₁ changes how often the trial stops early; moving r changes how much evidence a positive result requires. Altering either one changes the design's Type I error and power, which is why they are always reported as a set rather than one at a time.
Pre-specification is what makes the two-stage procedure valid. The interim result is allowed to affect whether the trial continues, but it is not allowed to affect the boundaries themselves. That is why early stopping must be pre-specified: only then do the error rates calculated at the design stage still describe the trial that is run.
Type I Error and Power
Formally, a single-arm Phase II trial tests H₀: p ≤ p₀ against the one-sided alternative H₁: p ≥ p₁, and the design is powered at p = p₁. Type I error and power therefore describe the whole two-stage procedure rather than a single test: H₀ is rejected only when the interim rule allows continuation and the total number of responses exceeds r. A positive result is evidence that the response rate is promising enough to justify further development, not evidence of clinical efficacy.
Because the two stages are treated as independent binomial samples, as in the published Simon design tables, the rejection probability at any response rate p can be written in closed form and evaluated exactly.
Evaluating this probability at p₀ gives the Type I error: the chance of calling an inactive treatment promising. Evaluating it at p₁ gives the power: the chance of calling a genuinely active treatment promising. A valid design keeps the first at or below α and the second at or above the target power, and choosing those two values is a clinical and portfolio decision rather than a statistical one.
Because n₁, r₁, N, and r are integers, the achieved error rates rarely equal the nominal values exactly. A design specified at α = 0.05 might achieve 0.0496, and a design targeting 80% power might achieve 0.8002. Both numbers are computed from the binomial distribution, not approximated with a normal distribution.
Probability of Early Termination (PET)
The probability of early termination is the chance that the trial stops after stage 1. It is the probability that the stage-one response count falls at or below the futility boundary, evaluated at the true response rate.
PET is a function of the true response rate rather than a fixed property of a design, so two evaluations usually matter. PET(p₀) describes how often an inactive treatment is abandoned after n₁ patients: the higher it is, the more patients are spared. PET(p₁) describes how often a genuinely promising treatment is stopped at the interim: the lower it is, the fewer opportunities are lost.
The two goals pull in opposite directions, and the balance between them is one of the operating characteristics that distinguishes otherwise valid designs. The dedicated article on the probability of early termination traces it across the response-rate range.
Expected Sample Size Under the Null Hypothesis
Expected sample size turns early stopping into an enrollment average. Trials that stop after stage 1 enroll n₁ patients; trials that continue enroll N. Weighting each outcome by its probability gives the expected total.
At p₀ this is the average number of patients the trial enrolls when the treatment is inactive. It is the quantity the optimal design minimizes, and it is usually well below N, because most inactive treatments stop at the interim.
Expected sample size and maximum sample size answer different questions: N bounds the trial, while EN(p₀) describes what it costs on average. Reporting one without the other hides the trade-off the design makes, which is why both belong in the protocol. Expected sample size can also be evaluated at p₁, where it approaches N because a promising treatment usually continues to stage 2.
A Worked Example: Optimal, Admissible, and Minimax Designs
Take p₀ = 0.20, p₁ = 0.40, α = 0.05, and 80% power: a common planning scenario for a single-arm oncology trial, and the row Simon tabulated in his 1989 paper, which makes the design easy to check against the published source.
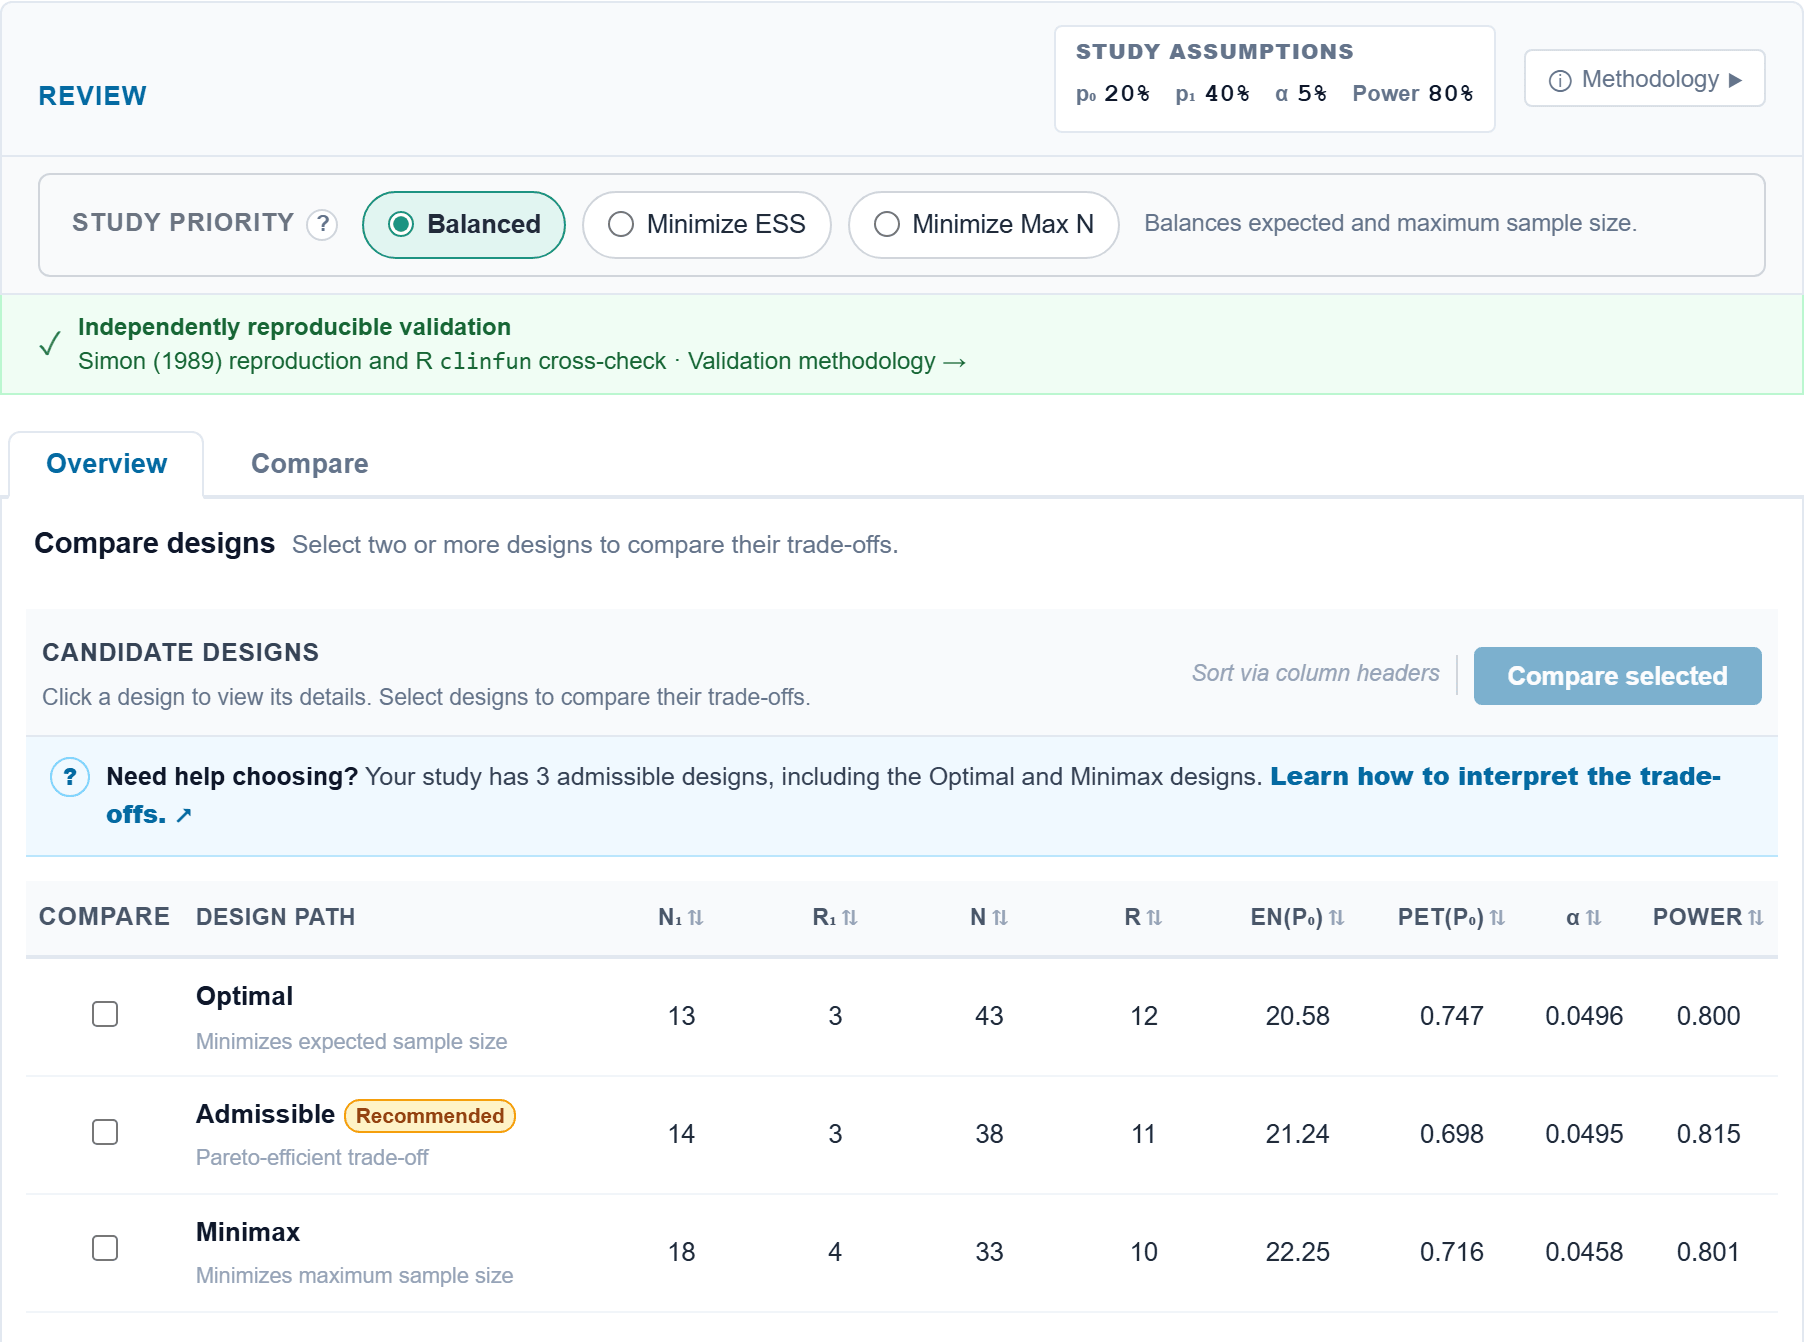
Because the boundaries are integers, the design is found by searching feasible values rather than by solving a formula. For each candidate the Type I error and power are computed exactly from the binomial distribution, and the designs below satisfy both constraints while no other candidate beats them on both maximum and expected sample size. Entering the same four assumptions in the BioStatHub workspace returns the same three candidates:
| Design | n₁ | r₁ | N | r |
|---|---|---|---|---|
| Optimal | 13 | 3 | 43 | 12 |
| Admissible | 14 | 3 | 38 | 11 |
| Minimax | 18 | 4 | 33 | 10 |
Stage 1: the early-stopping decision
Stage 1 enrols n₁ patients and counts responses. The optimal design stops at the interim if at most 3 of the first 13 patients respond; the admissible design applies the same boundary of 3 in 14 patients, and the minimax design stops if at most 4 of 18 patients respond.
Under p₀ = 0.20 the optimal design stops after stage 1 in 74.7% of trials, the minimax design in 71.6%, and the admissible design in 69.8%. Evaluated at p₁ = 0.40 the same boundaries stop 16.9%, 9.4%, and 12.4% of genuinely active treatments respectively. All three control the error rates; what differs is how the interim is placed.
Stage 2: the final success decision
If the interim count is above r₁, the trial continues and enrols the remaining patients up to N. The optimal design continues from 13 to 43 patients and declares the treatment promising only if the total number of responses is at least 13, which is the rule r = 12 written as a decision. The admissible design runs to 38 patients and needs at least 12; the minimax design runs to 33 and needs at least 11.
Early stopping therefore changes how many patients are enrolled before the decision, never the standard of evidence required for a positive conclusion: the final boundary is fixed before the first patient is enrolled.
For a second scenario worked through end to end — p₀ = 0.10 and p₁ = 0.30, with four candidate designs and the full PET, expected sample size, Type I error and power calculations — see the Simon's two-stage design example.
Why the optimal design can be the larger trial
The optimal design is not the design with the smallest maximum enrollment; it is the design with the smallest expected enrollment under p₀. Because it stops early more aggressively, with a boundary of 3 responses in 13 patients, it saves patients on average at the cost of a larger total when the treatment turns out to work.
It also stops a genuinely promising treatment at the interim 16.9% of the time (PET(p₁) = 0.169), against 9.4% for the minimax design. Both still reach their target power because the final boundaries differ: 13 or more responses among 43 for the optimal design, 11 or more among 33 for the minimax design.
How the Worked Example Meets Its Constraints
A valid design controls the error rates over the whole two-stage procedure, not at each stage separately: the null hypothesis is rejected only when the interim rule allows continuation and the final count exceeds r. Every trial therefore ends in exactly one of three ways, and the probability of each can be computed exactly for the optimal design:
| Outcome for the optimal design | At p₀ = 0.20 | At p₁ = 0.40 |
|---|---|---|
| Stop after stage 1 (x₁ ≤ 3) | 0.7473 | 0.1686 |
| Continue, then fail the final rule (x₁ > 3 and total ≤ 12) | 0.2031 | 0.0312 |
| Continue, then declare the treatment promising (x₁ > 3 and total ≥ 13) | 0.0496 | 0.8002 |
Achieved Type I error and power
The third row is the rejection probability. Evaluated at p₀ it is the Type I error, 0.0496, which is at or below the specified 0.05; evaluated at p₁ it is the power, 0.8002, which is at or above the target 0.80. The same computation for the other two designs gives 0.0495 and 0.8154 for the admissible design and 0.0458 and 0.8011 for the minimax design.
Because n₁, r₁, N, and r must be integers, a design specified at α = 0.05 rarely achieves exactly 0.05, and a design targeting 80% power rarely achieves exactly 0.80. A protocol table should report the achieved values, since those are what the trial actually guarantees.
Reproducing the numbers for a different set of assumptions means running the same search on new inputs and reading the achieved error rates, early-termination probability, and expected sample size from each candidate rather than from the nominal targets.
What the second stage costs
The second row is the price of the design. When the treatment is inactive, 20.3% of trials do not stop at the interim: they enrol all 43 patients and only then conclude that the response rate is too low. That is why expected enrollment under p₀ is 20.6 rather than 43, and why it is not 13 either.
At the target response rate the same accounting produces the Type II error. 16.9% of genuinely active treatments stop at the interim and a further 3.1% reach the full sample and still miss the final boundary; together they make up 1 − 0.8002 = 0.1998, the 20% chance of missing a treatment that works. Reading a design means reading all three rows, not only the rejection probability.
Minimax vs. Optimal Designs
The two named designs answer different questions. The minimax design asks what the smallest maximum number of patients can be; the optimal design asks what the smallest average number of patients is when the treatment is inactive. For the same p₀, p₁, α, and power, both satisfy the same error requirements, so the choice depends on the trade-off between expected and maximum enrollment.
The minimax design is the natural choice when the binding constraint is the maximum: recruitment is difficult, the eligible population is small, or budget, drug supply, or trial duration sets a hard ceiling.
The optimal design is the natural choice when the binding constraint is exposure under a treatment that probably will not work. Most single-arm Phase II treatments do not advance, so reducing the average number of patients exposed to an inactive therapy is often the more valuable saving, at the cost of a larger maximum and, in the example above, a higher chance of stopping a promising treatment early.
Neither design is statistically superior. The comparison is about which cost the study can absorb, not about which design is more defensible.
| Design | Maximum N | EN(p₀) | PET(p₀) |
|---|---|---|---|
| Optimal | 43 | 20.6 | 0.747 |
| Admissible | 38 | 21.2 | 0.698 |
| Minimax | 33 | 22.3 | 0.716 |
Which Simon Design Fits Your Trial?
Start with the constraint that actually binds. If the maximum enrollment is fixed by recruitment, budget, or a funder's limit, the design has to respect that ceiling, which means the design search and the sample size calculation have to agree.
Minimax designs prioritize limiting maximum enrollment. They are a natural choice when recruitment, budget, or drug supply is constrained.
Optimal designs prioritize expected enrollment under the null response rate. They tend to stop an inactive treatment after fewer patients.
Everything between those two positions is also valid. Admissible designs are the candidates that no other design beats on both maximum and expected sample size, so they are the place to look when neither extreme matches the study.
In the worked example, moving from the optimal to the minimax design removes ten patients from the maximum and adds fewer than two to the expected enrollment under p₀. Whether that is a good trade depends on what a patient slot is worth in your setting.
Whichever candidate you choose, record the comparison rather than the conclusion: maximum size, expected size, PET, achieved Type I error, and power for every design considered. A written rationale is easier to defend at protocol review than a single preferred output, and the criteria for how to choose between Simon designs are worth agreeing before the table is reviewed.
Looking Beyond Sample Size
Sample size is the headline number, but operating characteristics are what a protocol reviewer will ask about. Beyond N and EN(p₀), examine PET at both p₀ and p₁, expected enrollment at p₁, the achieved error rates, and the power curve across plausible response rates.
Feasibility matters as much as statistics. A two-stage design requires a real interim analysis: enrollment must pause, responses must be evaluable at the boundary, and the data must be clean enough to apply the rule. If the interim cannot be delivered operationally, a design that depends on it will not behave as planned.
Sensitivity is the last check. Response rates between p₀ and p₁ produce intermediate power, and small changes in p₀ can change which candidate is optimal. A design that looks strong under one precise assumption can be fragile under a plausible alternative.
Common Challenges
The same questions come up whenever a design is chosen: which candidate best matches the study, why several designs look equally defensible, how large the gap between expected and maximum enrollment really is, how sensitive the design is to the assumed response rates, and whether a published design can be reproduced.
Each of those questions is answered by comparing candidates rather than by generating one table. The frontier above shows why: every admissible design is the best available for some weighting of maximum against expected enrollment, so the comparison carries the decision.
Modern Tools Can Simplify the Process
Simon designs are available in statistical software, most commonly the R package clinfun and its ph2simon() function, which searches feasible designs and returns the optimal and minimax candidates with their operating characteristics. Published design tables remain useful for common planning scenarios.
Interactive tools run the same search with faster feedback: enter p₀, p₁, α, and power, and review the admissible frontier rather than a single answer. If you are planning a Phase II trial, you can generate and compare candidate Simon designs with the BioStatHub Simon's two-stage design calculator, then document the final choice in the same workspace. The step-by-step walkthrough of generating a design in BioStatHub covers the same workspace from assumption entry to export.
The value is not only speed. Seeing what each candidate costs before committing to one, and keeping a record of the comparison, is what turns a generated table into a design decision.
Final Thoughts
Simon's two-stage design remains a standard for single-arm Phase II trials because it does three things well: it controls Type I error and power at values chosen in advance, it stops inactive treatments early, and it produces an explicit decision rule that a reviewer can check.
Understanding the four parameters, the two boundaries, the probability of early termination, and expected sample size is what turns a list of candidates into a defensible design. The choice between optimal, minimax, and admissible designs is a judgement about maximum enrollment, average enrollment, and what the study can tolerate, not about which design is statistically correct.
More than thirty years after its introduction, the method is still in daily use because it matches how single-arm Phase II trials are actually run: a small first cohort, one planned look, and a decision that can be written into the protocol before the first patient is enrolled.
Frequently Asked Questions
What is Simon's two-stage design used for?
It is commonly used in single-arm phase II trials to test whether a treatment response rate is promising enough to justify further investigation while allowing early stopping for futility.
Does early stopping change the final success rule?
No. The design defines both the stage 1 futility rule and the final total-response rule before the trial starts.
Why is it called a two-stage design?
The trial has a planned first-stage interim look followed by a second stage only when the interim response count is high enough to justify continued enrollment.
What is PET in a Simon design?
PET is the probability of early termination. It is commonly evaluated under the null response rate because it describes how often an inactive treatment is expected to stop after stage 1.
What is ESS?
ESS is expected sample size. It accounts for both trials that stop after stage 1 and trials that continue to the maximum planned enrollment.
What is the difference between maximum and expected sample size?
Maximum sample size N is the largest number of patients the trial can enrol, and it is reached only when the trial continues past stage 1. Expected sample size EN(p₀) is the average across trials that stop early and trials that continue. In the worked example the optimal design has N = 43 but expects 20.6 patients when the treatment is inactive.
What are admissible designs?
Admissible designs are valid designs that balance the two usual extremes: the smallest maximum sample size and the smallest expected sample size under the null.
When should I choose a minimax design?
A minimax design is often useful when there is a hard cap on enrollment, budget, drug supply, or trial duration.
Can Simon's design be used outside oncology?
Yes. It is especially common in oncology, but the same two-stage framework can be used in other single-arm settings with a binary endpoint and appropriate design assumptions.
Does Simon's design require equal stage sizes?
No. The first-stage sample size and total sample size are chosen by the design search and do not have to split enrollment equally.
How do alpha and beta affect the design?
More stringent Type I error or Type II error constraints usually require larger sample sizes because the design must better separate the null and target response rates.